1. Causes of Atopic Dermatitis
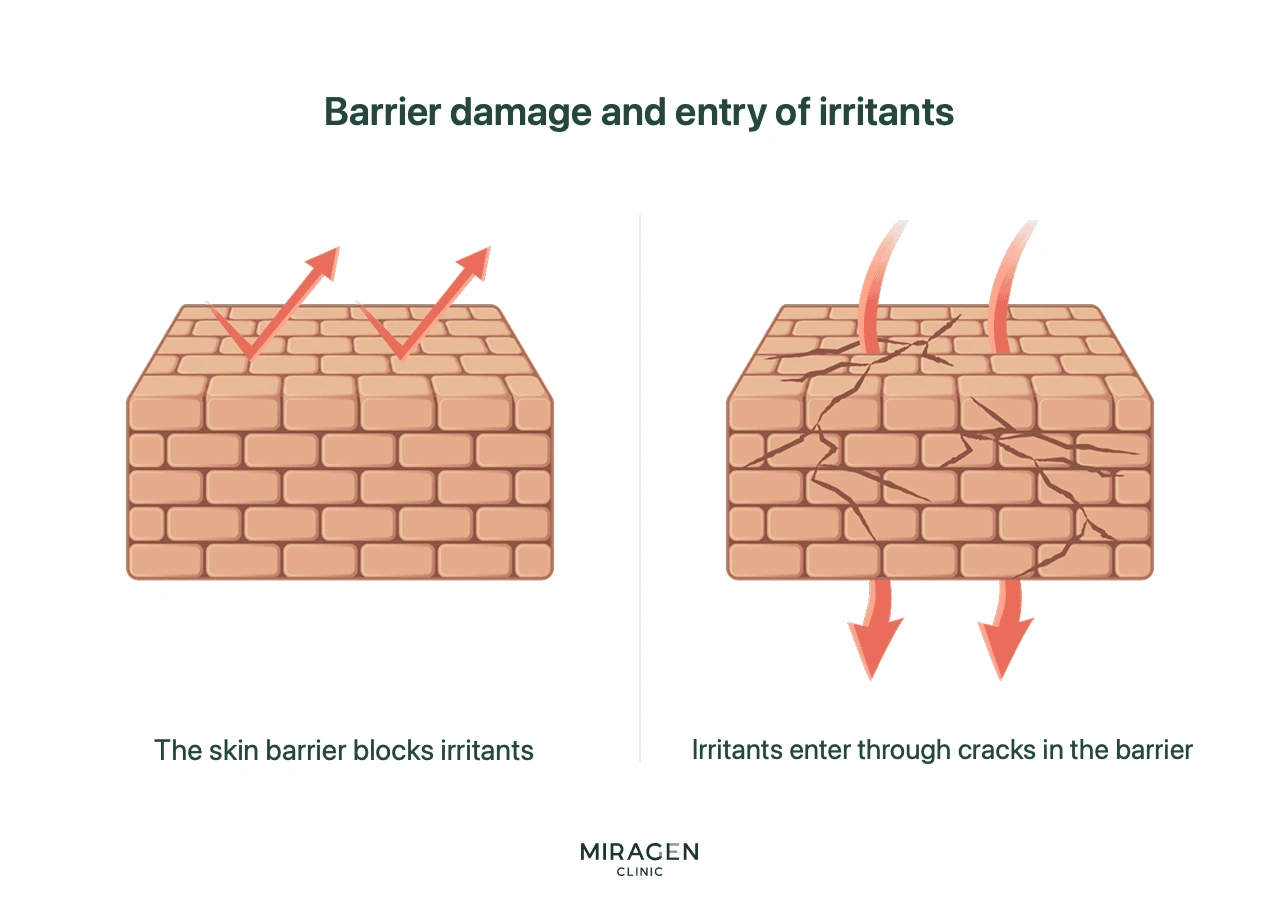
Atopic dermatitis is a condition that occurs when the skin barrier is weak, allowing external irritants to penetrate the skin.1
Congenital or acquired barrier defects are the starting point. As the barrier breaks down, the immune response becomes overactivated, leading to a vicious cycle where the overactive immunity further weakens the barrier.1 In this process, atopic dermatitis can also trigger immune abnormalities (allergies).
Pediatric Atopic Dermatitis
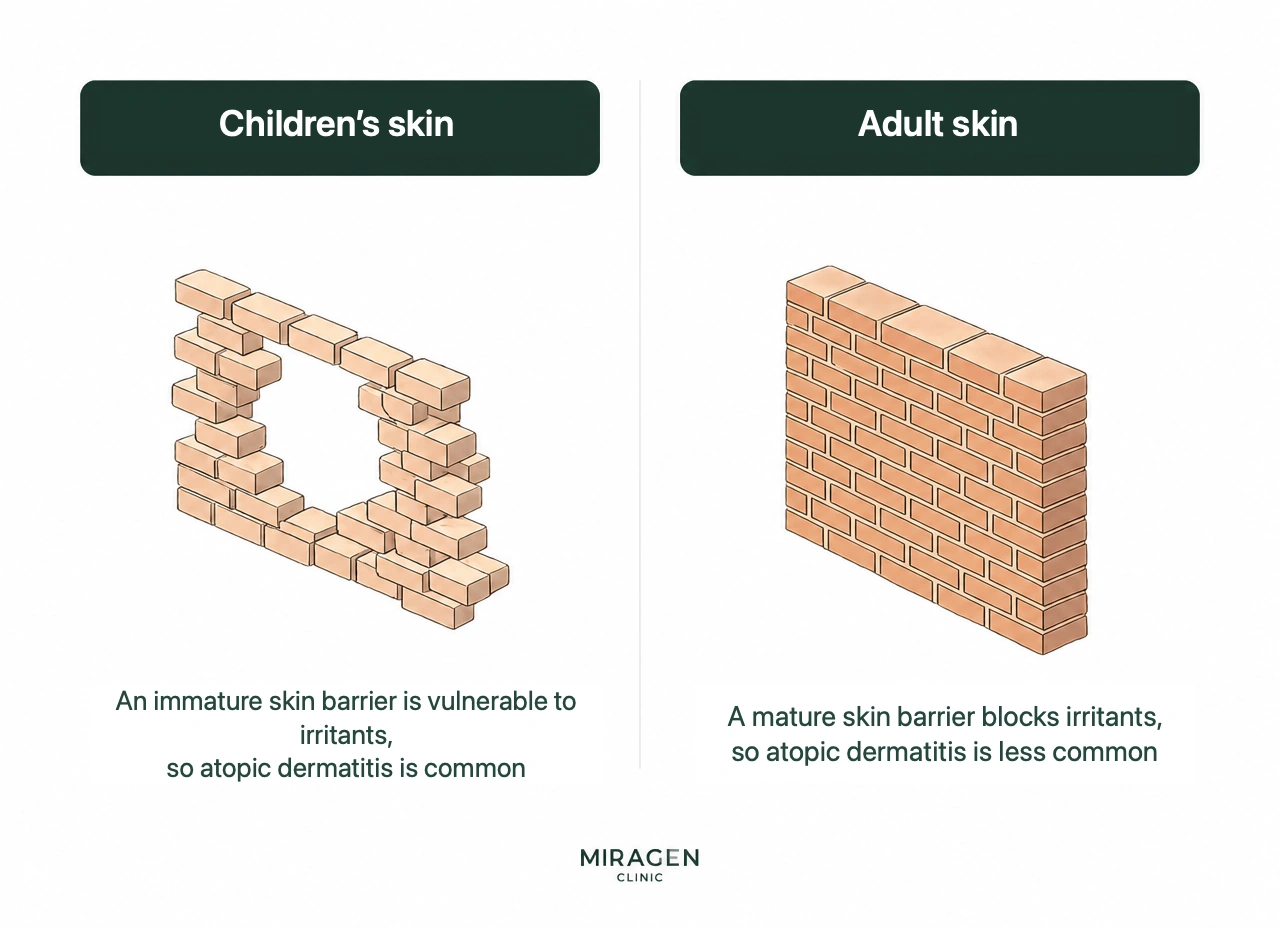
Atopic dermatitis is common in children because their skin barrier is immature and vulnerable to external irritants. In particular, if there is a filaggrin gene mutation, the barrier is even more fragile, significantly increasing the risk of onset.2 If you are unsure whether a rash on a baby’s face is heat rash or atopic dermatitis, please refer to our article on Distinguishing Newborn Atopic Dermatitis from Heat Rash.
Adult Atopic Dermatitis
In most cases, atopic dermatitis disappears as the skin barrier matures in adulthood. However, if the skin barrier is damaged by peels, lasers, waxing, home care devices, functional cosmetics (such as AHA/BHA/Retinol), steroid misuse, or occupational exposure to chronic irritants, atopic dermatitis can recur or develop for the first time.
2. Atopic Dermatitis, Rosacea, and Seborrheic Dermatitis: What are the differences?
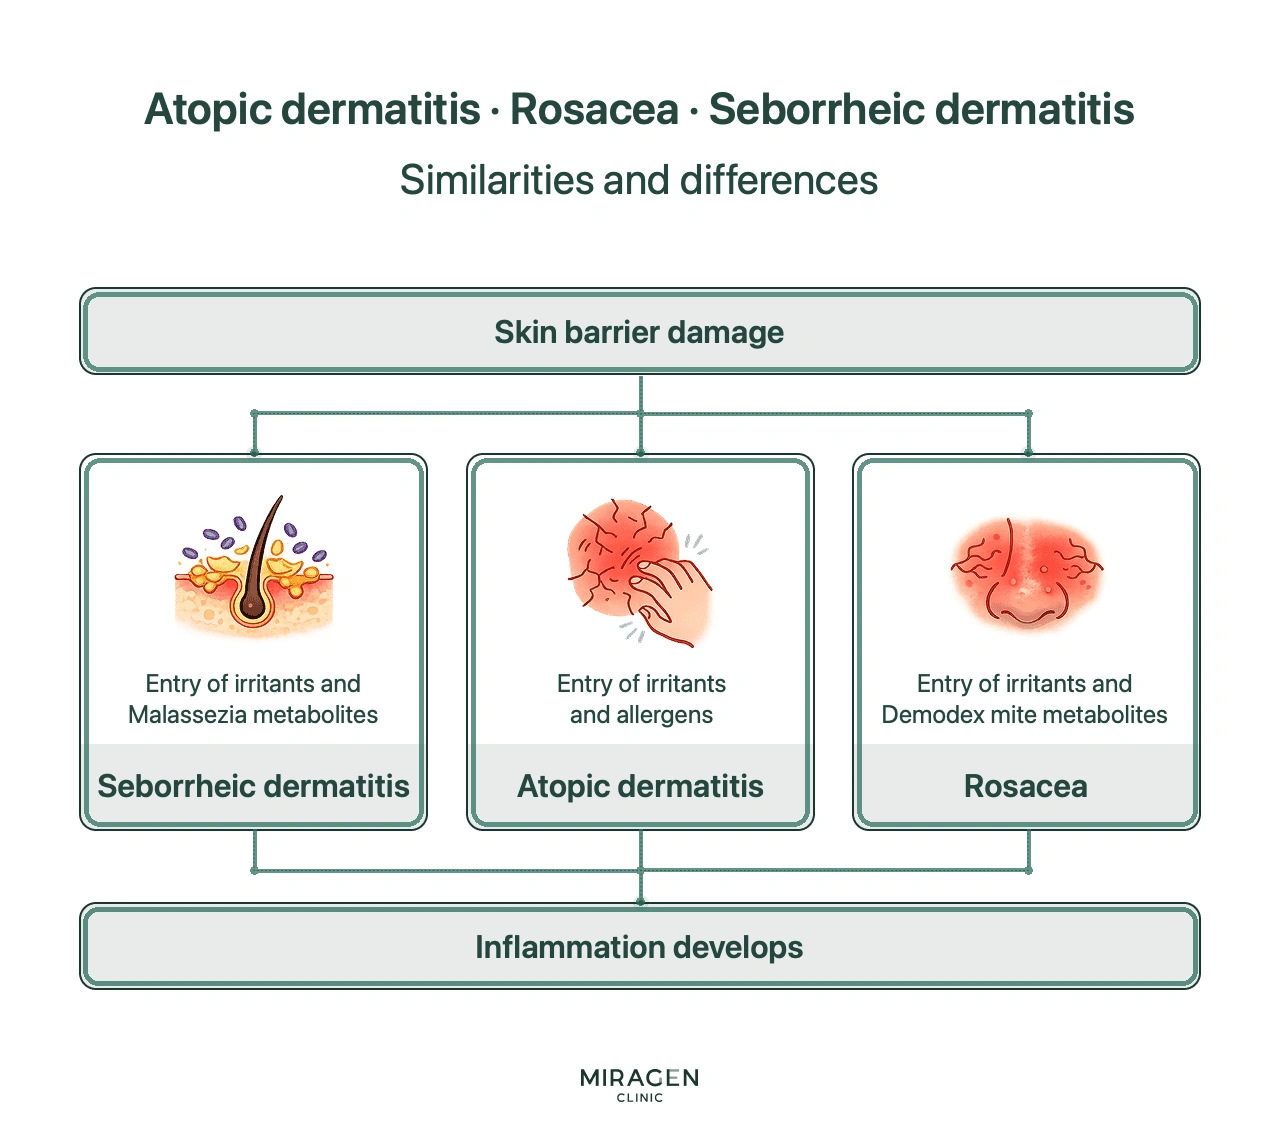
All three conditions share the commonality that the skin barrier is weak, making contact dermatitis prone to occur even from everyday irritants. In addition, each condition has its own unique aggravating factors.
- Atopic Dermatitis — Immune hypersensitivity reaction caused by the penetration of allergens (house dust mites, pollen, etc.)
- Rosacea — Vasodilation and inflammation caused by the penetration of Demodex mite metabolites
- Seborrheic Dermatitis — Inflammation caused by the penetration of Malassezia fungal metabolites
Since the fundamental cause is the same, the treatment principle of requiring barrier recovery is also shared. However, because the additional treatments tailored to each condition differ, an accurate diagnosis is crucial.
Detailed information on each condition can be found in the Rosacea Guide and the Seborrheic Dermatitis Guide.
3. Atopic Dermatitis and Allergies
Many people misunderstand atopic dermatitis as an allergic disease, but conversely, atopic dermatitis triggers allergies.3,4
3.1 Citizens and the Mafia
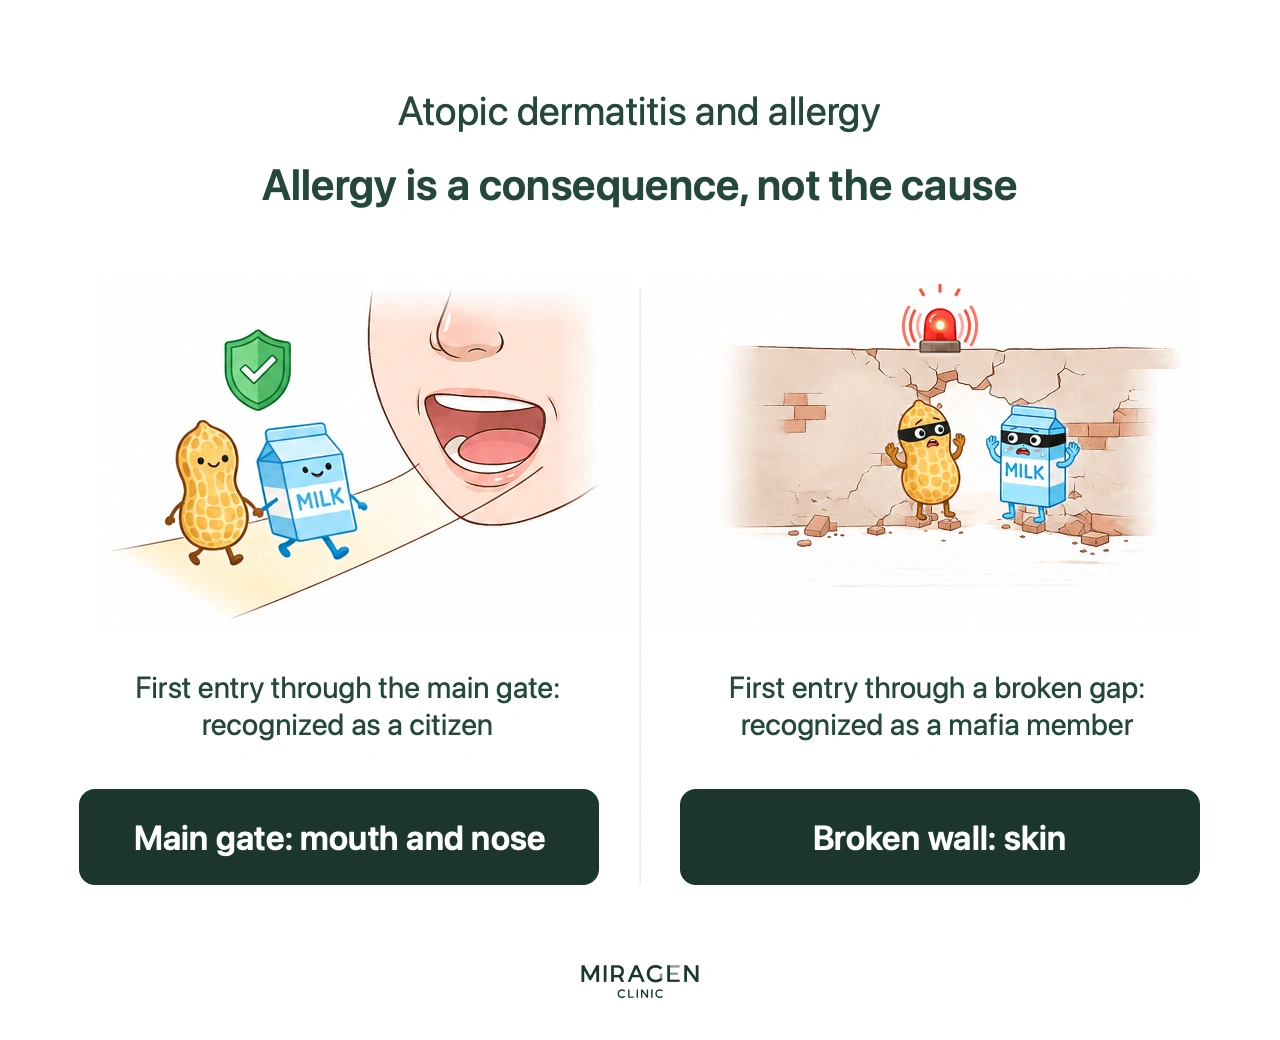
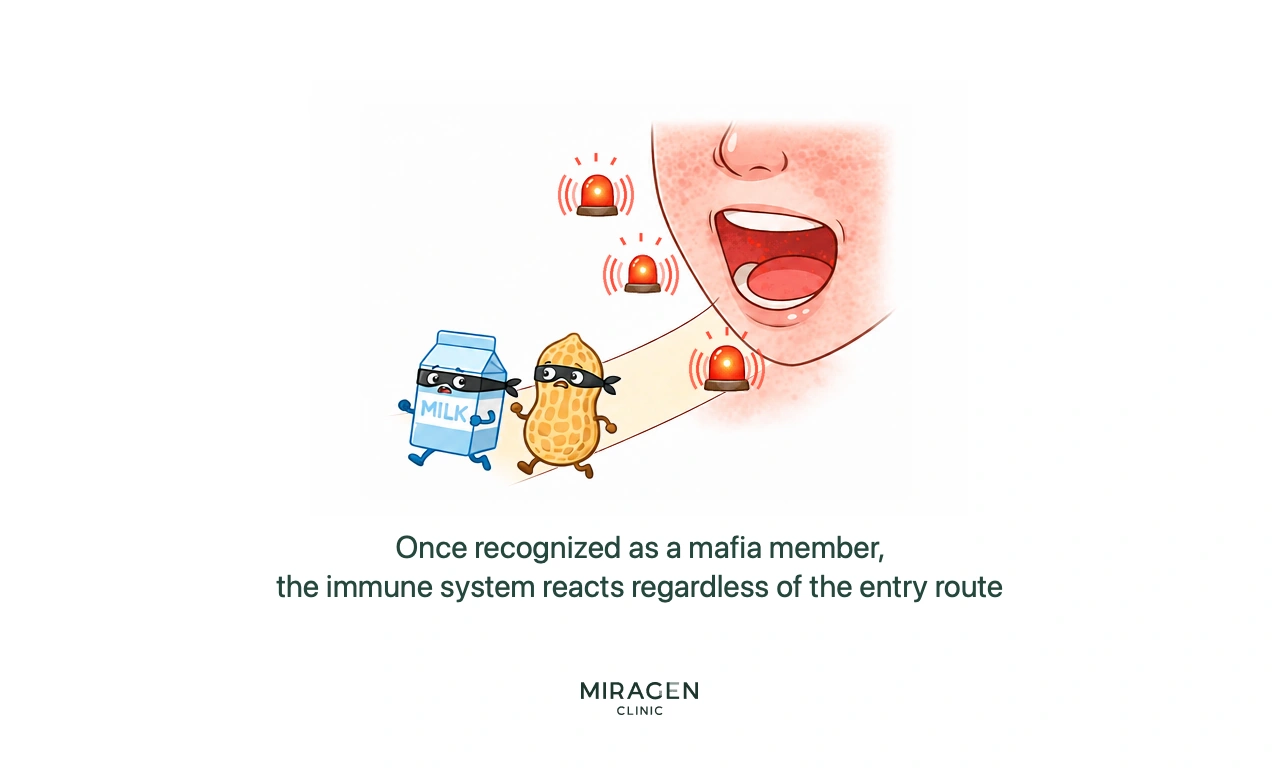
Our immune system recognizes substances that first enter through the ‘front gate’ (digestive or respiratory tract) as citizens (immune tolerance).
However, if the ‘fence’ (skin) is broken, some substances enter through the gaps first. In this case, the immune system recognizes those substances as the ‘Mafia.’
3.2 The Emergency Alarm
Once a substance is labeled as the Mafia, an emergency alarm (inflammation) rings throughout the body even if it enters through the front gate (food or respiration).
3.3 The Core of Treatment
Therefore, for atopic dermatitis accompanied by allergies, efforts to identify and avoid environmental allergens are necessary, in addition to skin care.
3.4 Atopic Dermatitis Without Allergies
However, not all atopic dermatitis is accompanied by allergies. It is called extrinsic if accompanied by allergies, and intrinsic if it is not.
Characteristics of Intrinsic Atopic Dermatitis
Intrinsic cases account for approximately 20% of all atopic dermatitis and are characterized by normal serum IgE levels during acute allergy testing (MAST test), with no sensitization to environmental allergens.5
This occurs because the skin barrier issues developed after the list of Citizens and Mafia had already been finalized; therefore, it is not accompanied by allergies.

Because the immune system ignores external substances entering through the fence, thinking “It’s just a citizen,” there are many cases where the damage to the fence is severe compared to the symptoms.
However, since one can focus on repairing the broken fence rather than environmental management, treatment is generally easier than in cases accompanied by allergies (extrinsic).
4. Atopic Dermatitis and Food
The relationship between atopic dermatitis and food differs significantly between children and adults.
Since childhood is a period when the immune system learns to react to food, it is more important to establish immune tolerance by introducing a variety of foods early on, rather than imposing indiscriminate dietary restrictions, unless there is a severe allergic reaction.6
Adults are not as affected by food as children, but caution is needed as foods high in histamine, foods high in nickel (if a nickel allergy exists), sugar, and alcohol can worsen symptoms.7
Our article on foods for atopic dermatitis reviews the evidence on probiotics, vitamin D, sugar, flour, dairy, and caffeine.
For IgG4 delayed allergy testing, see our delayed allergy test guide.
5. Steroid Ointments
Steroid ointments can suppress inflammation quickly and powerfully, but they can also weaken the skin barrier. Therefore, they must be used carefully, considering the potency grade, application site, and barrier condition.8
Repeatedly scratching and rubbing the same area because of atopic dermatitis can make the skin thick and hard. This is called lichenification.
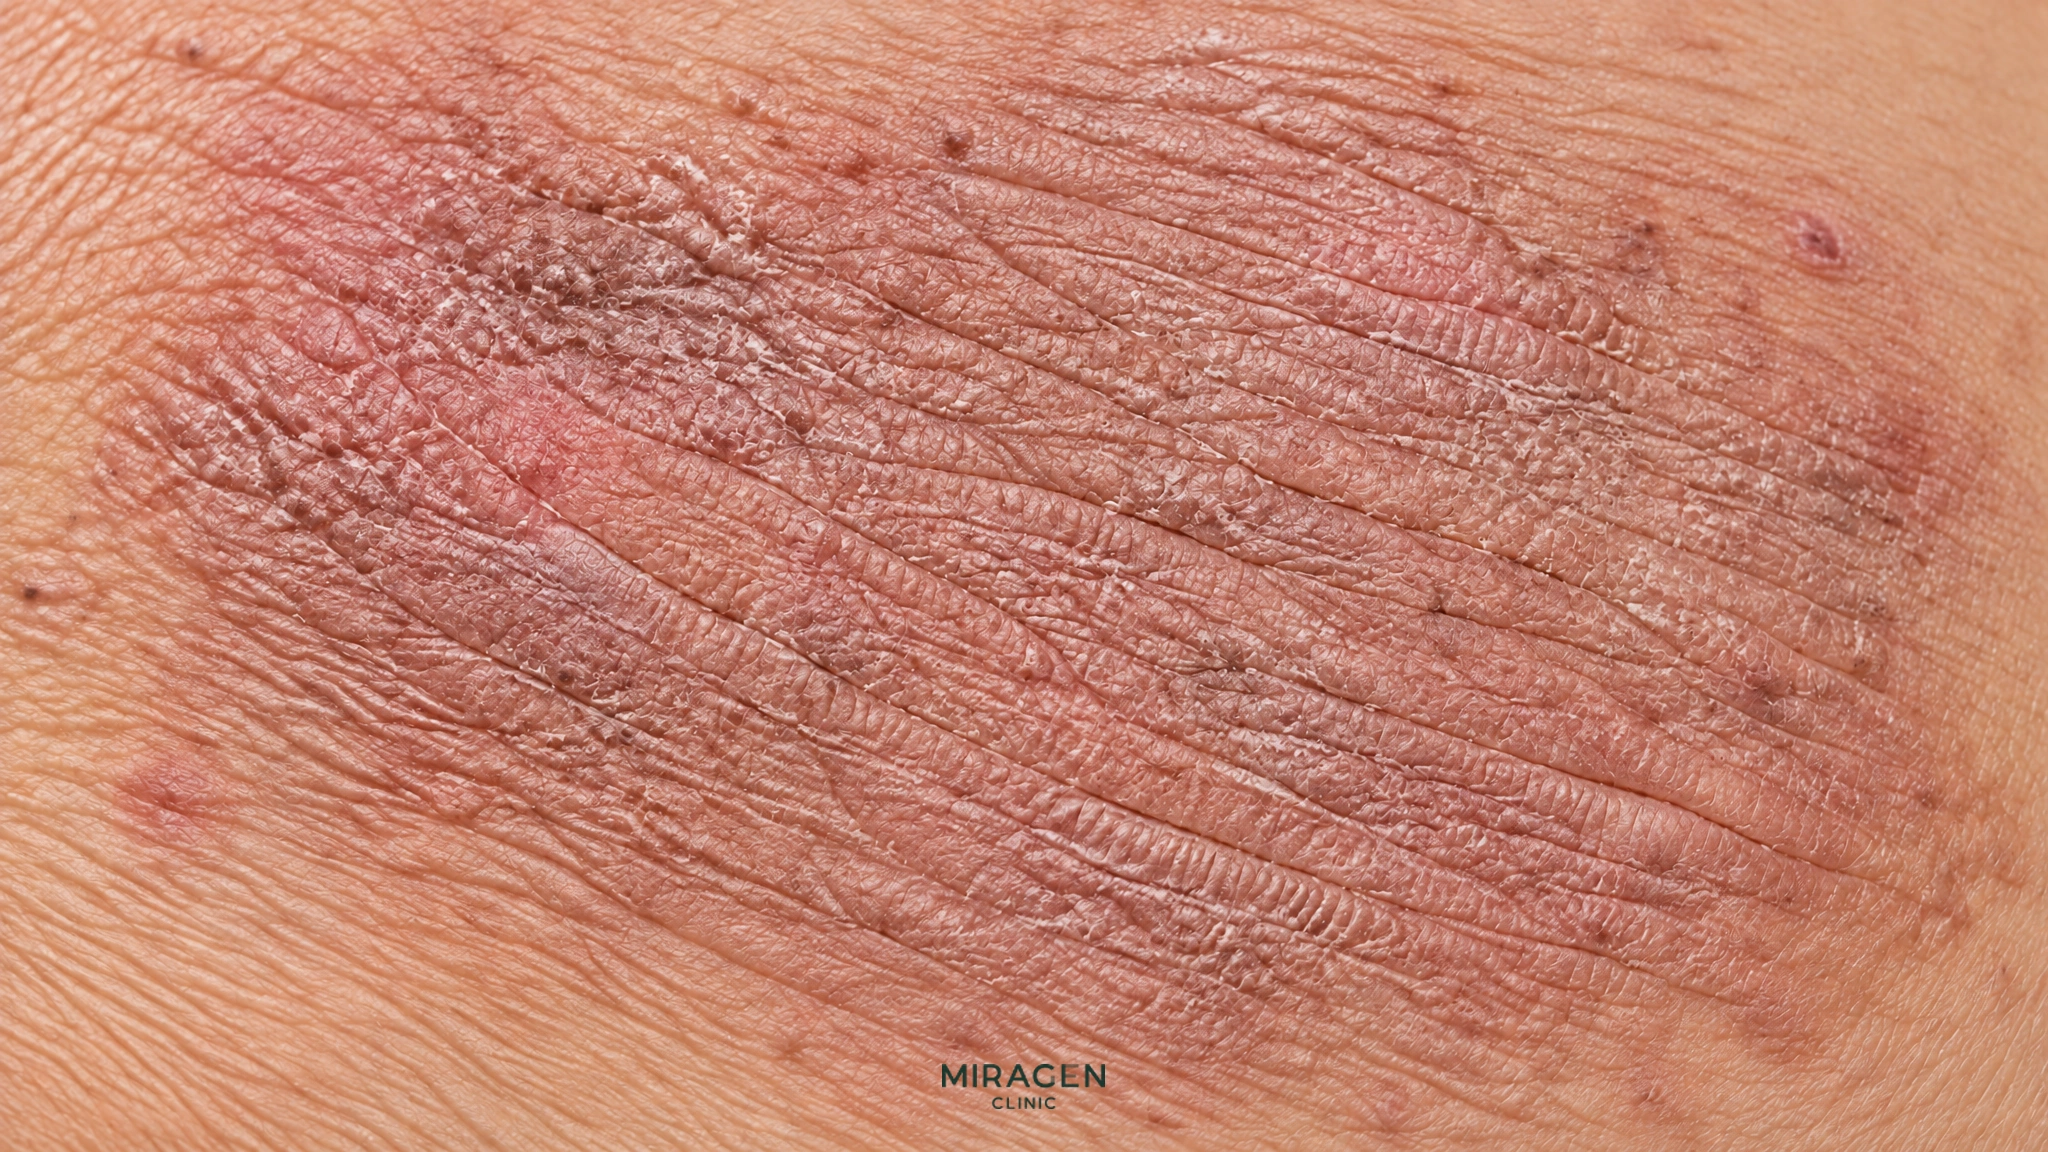
At our clinic, we mainly prescribe steroid ointments to help these areas recover. Lichenified skin can quickly become thinner and softer with a steroid ointment. Once its thickness returns to normal, nonsteroidal ointments such as Protopic may also penetrate better.
Do not apply a steroid on your own to an area that newly feels thick or hard. Use it only on the areas and for the period decided during your visit, and reassess which areas still need it as the skin changes.
See the topical steroid guide for use instructions and the steroid ointment grades article for product potency.
6. Protopic and Elidel
Protopic and Elidel are non-steroidal anti-inflammatory agents that can be used instead of steroids. They are useful in situations requiring long-term management, such as atopic dermatitis, because they do not weaken the skin barrier.9
However, when the skin barrier is weak, excessive absorption can lead to contact dermatitis; therefore, it is advisable to check sensitivity with a patch test before use.
Detailed information can be found in the Elidel Guide and the Protopic Guide.
7. Antihistamines
Many people with atopic dermatitis take antihistamines to ease itching. But the itch of atopic dermatitis differs from that of hives. Histamine plays a major role in the itch of hives, whereas blocking histamine alone does not adequately ease atopic dermatitis itch.
7.1 Why prescribe antihistamines, then?

First-generation antihistamines also block histamine receptors in the brain and cause drowsiness. Some people who cannot sleep because of itching find it less difficult to get through the night when the medication makes them sleepy.
However, feeling drowsy is different from actually improving itch or a sleep disorder. First-generation antihistamines should not replace dermatitis treatment or be regarded as medicines to take every day for a long time. Even when taken at night, watch for drowsiness or reduced concentration the following day.
Our Peniramin article explains nighttime use, adverse effects, and related studies. For differences among antihistamines, see our antihistamines article.
8. Moisturizers
Moisturizers support the skin barrier by reducing water loss and blocking external irritants. Yet when the barrier is weak, more of a moisturizer's ingredients can enter the skin and cause irritation, so finding a suitable one matters.10,11
8.1 Why does a moisturizer that used to work now sting?
When the skin barrier weakens, even ingredients in a moisturizer that used to work well can cause contact dermatitis. When dermatitis is severe enough to ooze, some people feel more comfortable without moisturizer.
A poorly tolerated moisturizer contributes to many cases of what patients call “ointment rebound.”
A moisturizer can also form a protective film on the skin, support barrier function, and help recovery. This is why finding one that suits your skin matters. Our article on steroid ointment side effects explains the link between moisturizers and recurring dermatitis in more detail.
8.2 How we find a suitable moisturizer
At our clinic, we use patch tests to check sensitivity to several MD creams and offer samples of products that may be suitable. We then look at how each product feels and how the skin responds during actual use to find one that can be used consistently.
If you suspect that a moisturizer is irritating your skin, stopping it for about three days and watching for a change may help. If symptoms improve, the moisturizer you were using may have been irritating the skin.
However, stopping moisturizer also removes its protective support for the skin barrier, so going without it can itself worsen symptoms. Thus, a lack of improvement after stopping does not prove that the moisturizer suited your skin. Both the removal of irritation and the loss of protection need to be considered.
See our article on going without moisturizer for the reasoning and precautions. For more on selecting moisturizers and MD creams, see the MD cream guide.
9. Managing Irritants in Daily Life
9.1 Laundry Detergents and Fabric Softeners
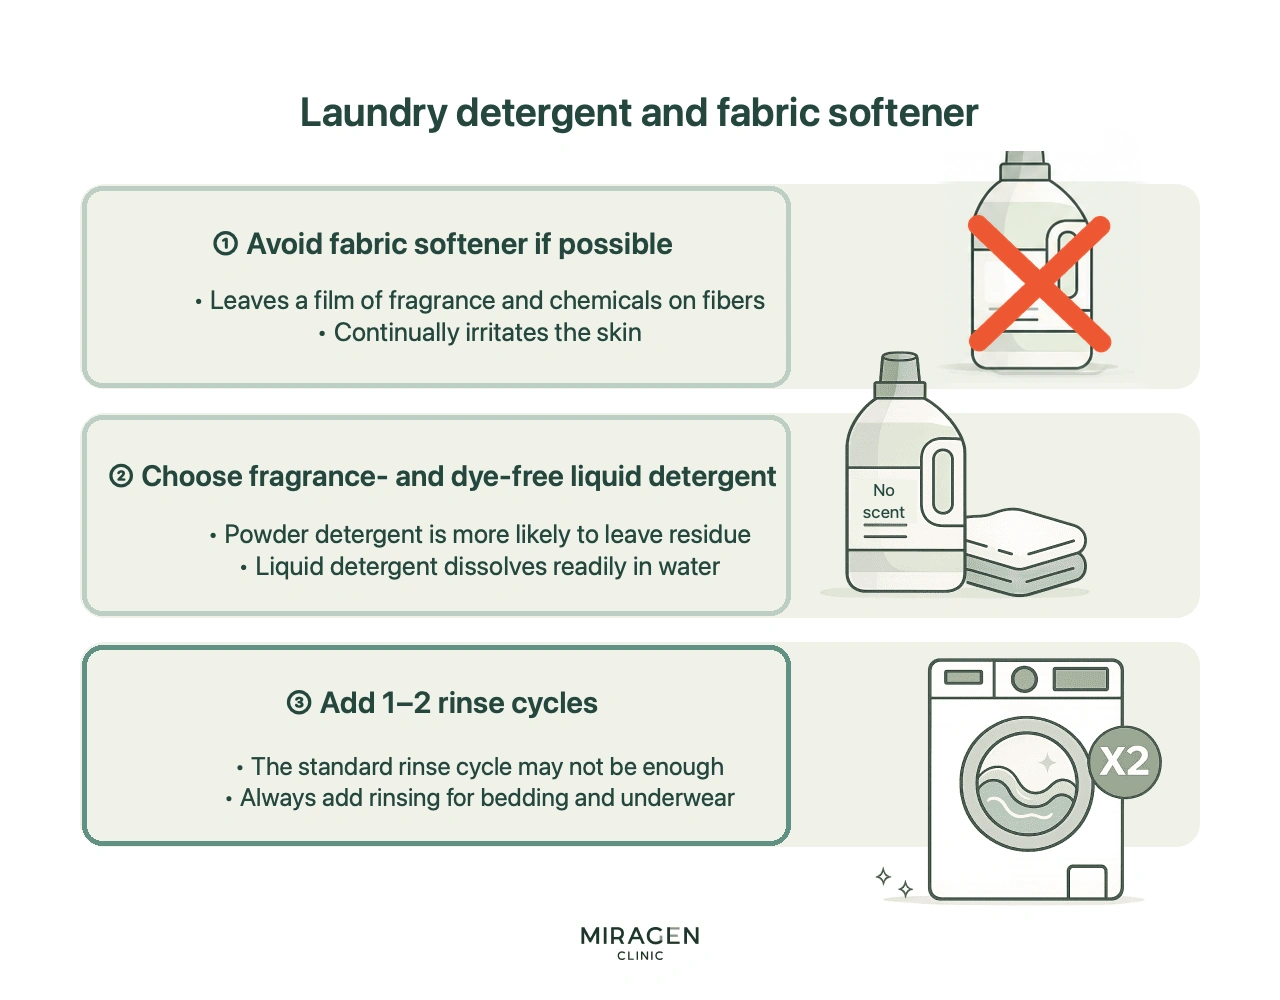
Detergent residue and fabric softeners left on clothes worn daily and blankets used overnight gradually break down the skin barrier.12
- Avoid using fabric softeners if possible: The principle of fabric softeners is to coat the fiber surface with a film of ‘fragrance’ and ‘chemical components.’ These ingredients cause continuous irritation to the skin.
- Liquid Detergent + Fragrance-free/Dye-free: Liquid detergents, which dissolve well in water, leave less residue than powder detergents. We recommend products that are ‘free of fragrances and dyes’ rather than those that ‘smell good.’
- Sufficient Rinsing: You should add 1–2 extra rinse cycles beyond the washing machine’s default setting to completely remove residual detergent components.
9.2 Perfumes and Fragrances
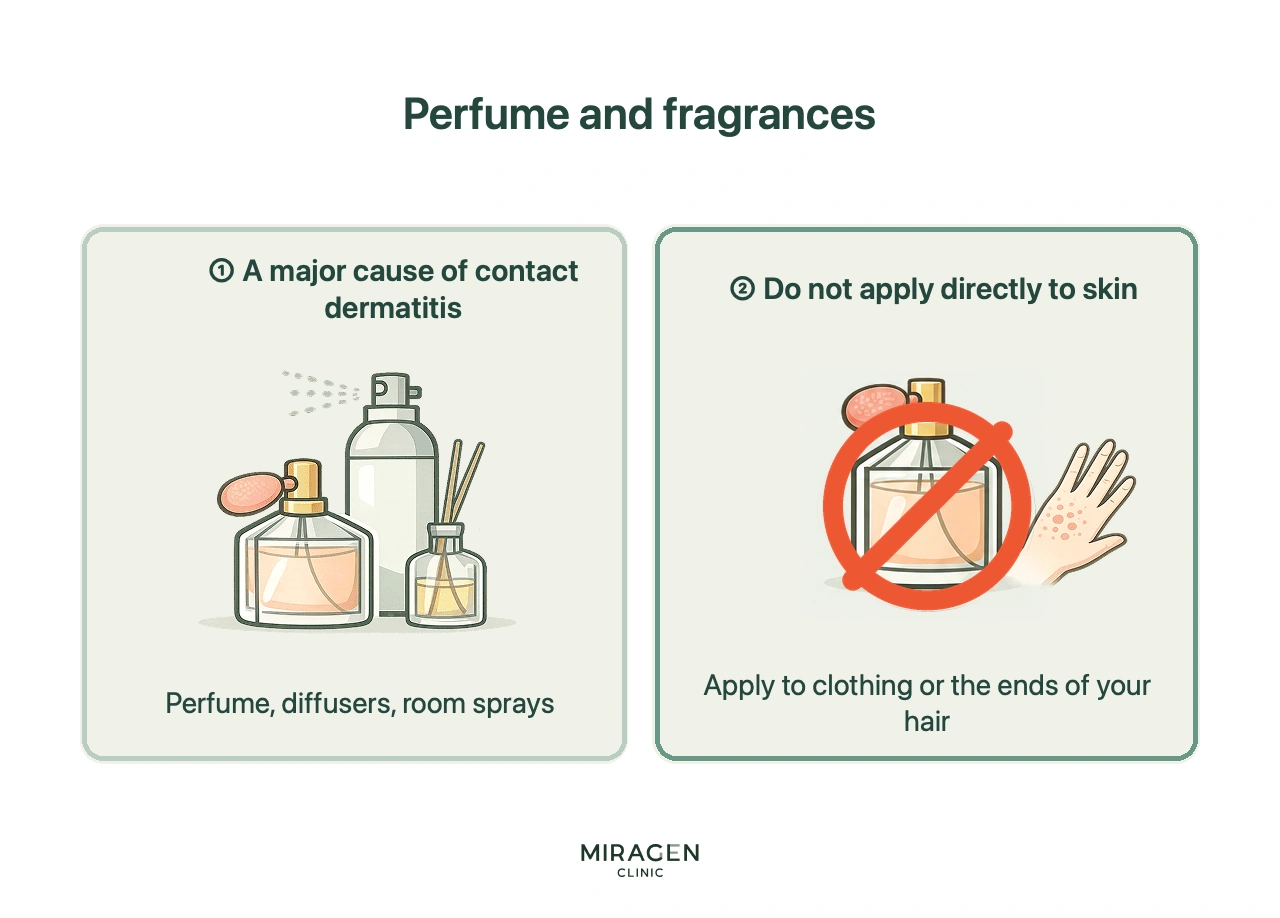
- The Main Culprit of Contact Dermatitis: Perfume is one of the most common causes of allergic contact dermatitis.13 Not only perfumes, but also fragrance components floating in the air from diffusers and room sprays can settle on the skin and cause irritation.
- No Direct Application: When the skin barrier is unstable, you must absolutely avoid spraying perfume directly onto the skin. If you want a scent, consider alternatives such as using a small amount on clothes or the ends of your hair instead of the skin.
9.3 Other Lifestyle Habits
- Minimize Cosmetics: It is best to refrain from using sunscreen or cosmetics until the skin barrier is fully recovered. They can seep into the skin and worsen inflammation.
- Watch Your Body Temperature: Increased body temperature from alcohol, spicy food, saunas, baths, or hot showers can increase blood flow to the skin and worsen inflammation.
- Proper Cleansing and Showering: It is very important to wash off irritants on the skin. Be sure to wash your face and shower every morning and evening, and wash immediately if exposed to external irritants. However, harsh cleansers or hot water will further break down the barrier. If the barrier is significantly weakened, focus on washing with water and use lukewarm water.
- Masks and Air Purifiers: If you have allergies to respiratory antigens, wear a mask when going out and run an air purifier indoors to minimize allergen exposure.
10. Our treatment approach
We consider the recovery of the skin barrier to be more important than simply suppressing inflammation.
To achieve this, we provide guidance on lifestyle habits to reduce external irritation after performing MAST tests, patch tests, and skin barrier function tests, and we perform concurrent treatments to protect the skin barrier.
First visit
1. Acute allergy test (MAST)
Identify factors that cause inflammation.

Translation of visible Korean original The visible heading reads “MAST Allergy test report.” Patient information and test results are blurred and cannot be read.
2. Delayed allergy test (patch test)
Check sensitivity to Protopic, Elidel, and MD creams.

3. Skin barrier function test (TEWL)
Assess how much the skin barrier's ability to prevent external irritants from entering and moisture from escaping has been impaired.
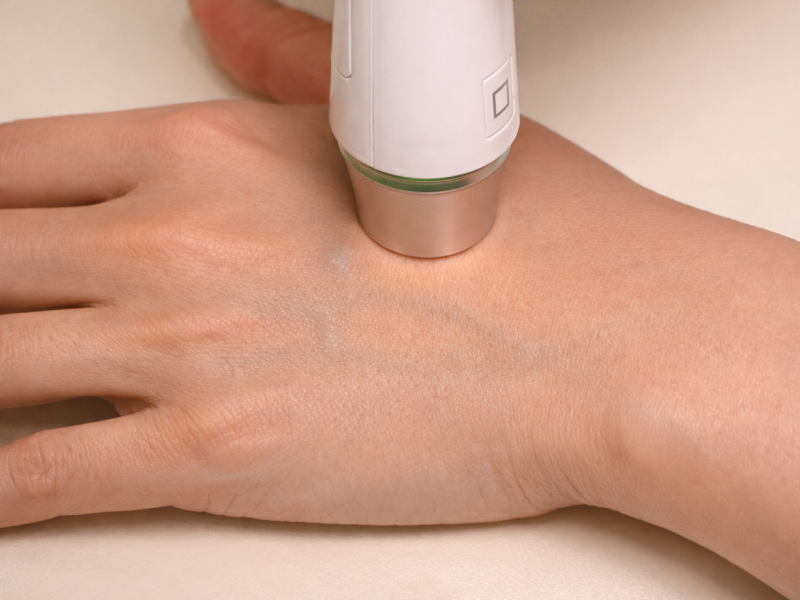
4. Skin barrier improvement
Protect the skin barrier with Skincellon (a wound dressing).
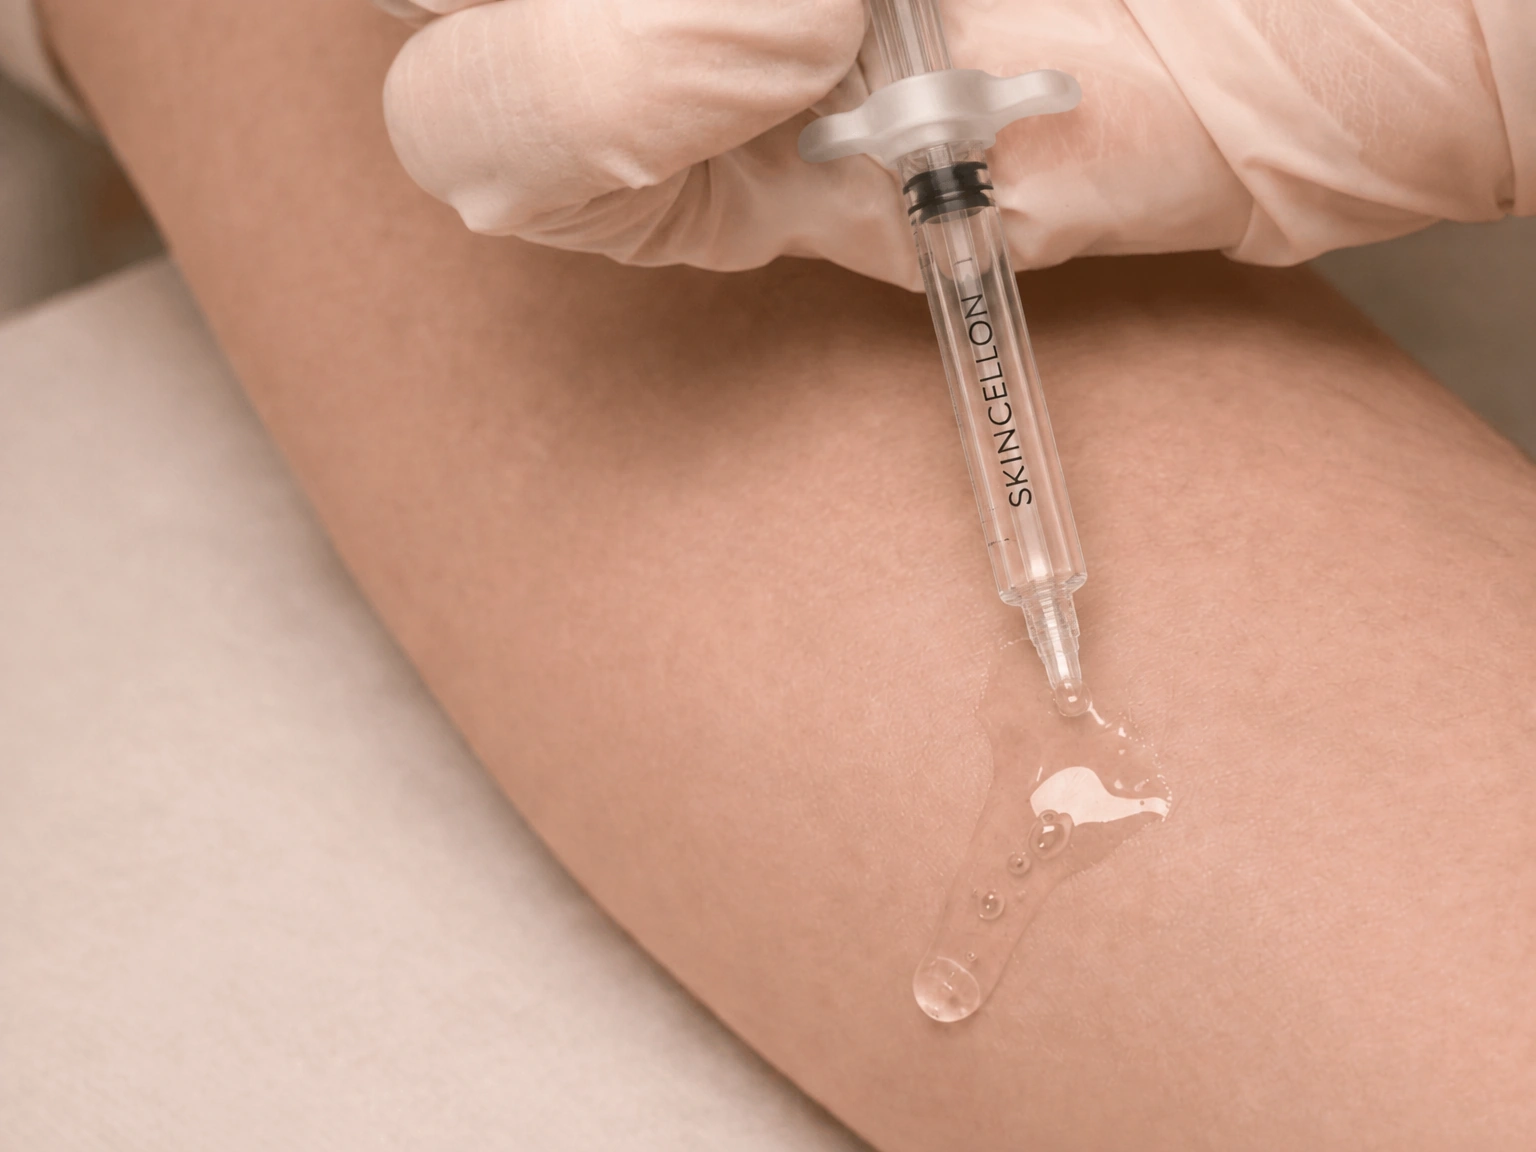
Second visit
1. Lifestyle guidance
Provide guidance on changes to the living environment based on the test results.

2. MD cream samples
Provide samples of MD creams that did not cause a sensitivity reaction.

3. Ointment prescription
Use ointments that did not cause sensitivity reactions to manage inflammation, Demodex mites, or fungi as needed.
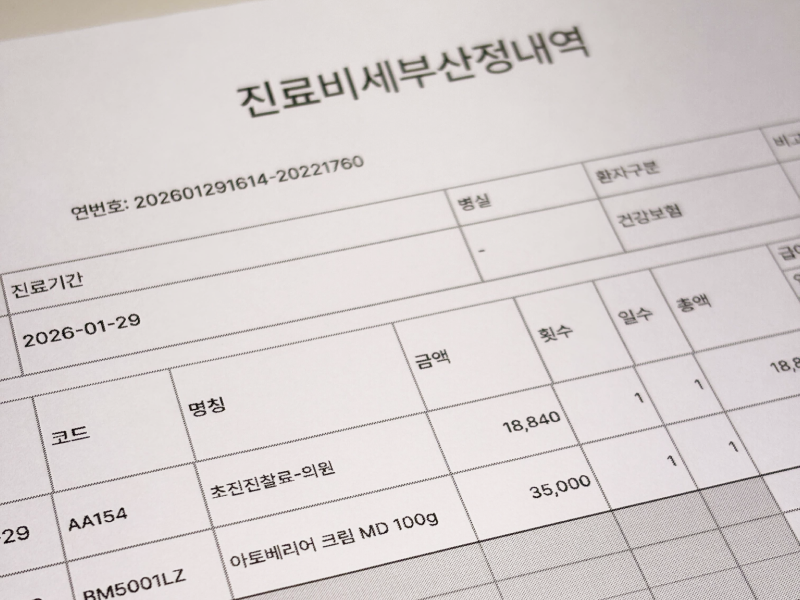
Translation of visible Korean original Itemized medical bill. Serial number: 202601291614-20221760. Date of care: 29 January 2026. Patient category: health insurance. Code AA154: initial consultation fee at a clinic, 18,840. Code BM5001LZ: Atobarrier Cream MD 100 g, 35,000. The currency unit and other fields are not readable in this crop.
4. Skin barrier improvement
Protect the skin barrier with Skincellon (a wound dressing).
Conclusion
Atopic dermatitis is a chronic inflammatory disease that begins with skin barrier damage. Once the barrier is restored and external irritants can no longer penetrate easily, you can become relatively free from the various restrictions mentioned above.
Therefore, our treatment goal is not temporary relief of atopic symptoms, but the reconstruction of a strong ‘skin fortress’ that protects itself.
Frequently Asked Questions
Can atopic dermatitis be cured?
The fundamental cause of atopic dermatitis is a weak skin barrier. When the skin barrier becomes strong, external irritants cannot penetrate, leading to improved symptoms; this state can be maintained long-term unless a specific event occurs. Furthermore, pediatric atopic dermatitis often improves naturally as the skin barrier matures with growth. Adults can also maintain a symptom-free state by removing the causes of barrier damage (such as steroid misuse, excessive skin procedures, and irritating cosmetics) and through consistent management.
I still itch after taking antihistamines for atopic dermatitis. Why?
Unlike hives, atopic dermatitis itch does not improve enough by blocking histamine alone. Some people feel that the drowsiness caused by a first-generation antihistamine makes nights less difficult, but drowsiness is different from an improvement in itch or a sleep disorder. It should not replace dermatitis treatment, and you should watch for next-day drowsiness or poor concentration. See the Peniramin article for details.
What makes a good moisturizer for atopic dermatitis?
The suitable product differs from person to person. Even a product that once worked well can irritate skin when the barrier weakens. At our clinic, we patch-test sensitivity to several MD creams and provide samples. We then look at how each feels and how the skin responds in actual use to find one that can be used consistently.
Can prolonged use of steroid ointment thin the skin?
Yes. It can thin the skin and weaken the barrier. At our clinic, we mainly use it to help thickened, hardened areas caused by repeated scratching recover. Follow the areas and duration decided during your visit, and reassess which areas need continued application as the skin changes.
Why does the skin worsen again after stopping steroid ointment?
If you stop the ointment while still exposed to a cause of inflammation, the inflammation that it suppressed may become apparent. In my practice, a common cause is a moisturizer that does not suit the skin. Alongside calming inflammation with an ointment, finding a suitable moisturizer therefore matters. See our article on steroid ointment side effects for details.
My child has atopy; is it okay to feed them eggs and milk?
Unless there are severe allergic reactions such as vomiting or hives, it is actually important to introduce them in small amounts. Since childhood is a period when the immune system ‘creates a list of citizens versus the mafia,’ the immune system must be educated to recognize food entering the digestive tract as a safe substance (immune tolerance). In a study of 640 subjects, the group with early peanut consumption had an approximately 81% lower incidence of allergies compared to the avoidance group. Excessive dietary restriction can actually increase the risk of allergies and hinder growth.
Are atopy and allergies the same thing?
No, they are not. Atopy, which occurs due to a weak skin barrier, is the cause, and an allergy is the result. When external substances penetrate through gaps in a weakened skin barrier, the immune system recognizes them as dangerous; subsequently, an allergic reaction occurs even when the same substance enters through food or respiration. However, not all patients have allergies; approximately 20% have ‘intrinsic’ atopy, which involves skin barrier issues without allergies.
References
- Elias PM, Hatano Y, Williams ML. Basis for the barrier abnormality in atopic dermatitis: outside-inside-outside pathogenic mechanisms. J Allergy Clin Immunol. 2008;121(6):1337-1343.
- Palmer CN, Irvine AD, Terron-Kwiatkowski A, et al. Common loss-of-function variants of the epidermal barrier protein filaggrin are a major predisposing factor for atopic dermatitis. Nat Genet. 2006;38(4):441-446.
- Lack G. Epidemiologic risks for food allergy. J Allergy Clin Immunol. 2008;121(6):1331-1336.
- Kubo A, Nagao K, Amagai M. Epidermal barrier dysfunction and cutaneous sensitization in atopic diseases. J Clin Invest. 2012;122(2):440-7.
- Schmid-Grendelmeier P, Simon D, Simon HU, et al. Epidemiology, clinical features, and immunology of the intrinsic (non-IgE-mediated) type of atopic dermatitis (constitutional dermatitis). Allergy. 2001;56(9):841-849.
- Du Toit G, Roberts G, Sayre PH, et al. Randomized trial of peanut consumption in infants at risk for peanut allergy. N Engl J Med. 2015;372(9):803-813.
- Katta R, Schlichte M. Diet and dermatitis: food triggers. J Clin Aesthet Dermatol. 2014;7(3):30-36.
- Coondoo A, Phiske M, Verma S, et al. Side-effects of topical steroids: A long overdue revisit. Indian Dermatol Online J. 2014;5(4):416-425.
- Czarnecka-Operacz M, Jenerowicz D. Topical calcineurin inhibitors in the treatment of atopic dermatitis – an update on safety issues. J Dtsch Dermatol Ges. 2012;10(3):167-172.
- Cork MJ, Robinson DA, Vasilopoulos Y, et al. New perspectives on epidermal barrier dysfunction in atopic dermatitis: gene-environment interactions. J Allergy Clin Immunol. 2006;118(1):3-21; quiz 22-3.
- Rastogi S, Patel KR, Singam V, et al. Allergic contact dermatitis to personal care products and topical medications in adults with atopic dermatitis. J Am Acad Dermatol. 2018;79(6):1028-1033.e6.
- Tanzer J, Meng D, Ohsaki A, et al. Laundry detergent promotes allergic skin inflammation and esophageal eosinophilia in mice. PLoS One. 2022;17(6):e0268651.
- Cheng J, Zug KA. Fragrance allergic contact dermatitis. Dermatitis. 2014;25(5):232-245.

